Open planner, pen and phone on a bright table by a sheer-curtained window with green plants, a calm setting for preparing questions before calling a treatment program

For a person whose first language is not English, the hardest part of residential mental health treatment can be something no brochure mentions: describing what is happening inside your own head in a language that does not quite fit. Words like “numb,” “on edge” or “racing thoughts” do not always have a clean equivalent, and a person who is already exhausted by depression, anxiety or trauma may fall back on “I’m fine” because it is the easiest English phrase available. This guide explains how language access usually works in residential care, where the gaps tend to be, and the specific questions to ask before admission.

Why Language Matters More in Mental Health Care Than Almost Anywhere Else

In most of medicine, a lab value or an X-ray carries much of the diagnostic weight. In mental health care, the main diagnostic tool is conversation. A psychiatric provider is listening for how long a low mood has lasted, whether sleep changed, whether worry feels controllable, whether a memory intrudes without warning. Each of those depends on fine distinctions in wording.

Families often notice the problem before clinicians do. A daughter hears her father tell a doctor he is “a little tired,” when at home he has stopped eating with the family and sits in the dark for hours. A husband watches his wife nod through an appointment she did not fully follow because she did not want to slow it down. These are not failures of honesty. They are what happens when someone is asked to describe distress in a second language while under strain.

The National Institute of Mental Health suggests preparing a list of questions to decide whether a provider is a good fit, including what experience they have treating someone with your issue and how long treatment is expected to last (NIMH: Help for Mental Illnesses). For a family that needs language support, that list should also include questions about how the program communicates.

Three Ways Programs Provide Language Access

Residential programs tend to use one or more of the following. They are not equal, and many programs combine them.

Bilingual clinicians: A therapist or psychiatric provider who speaks your language conducts sessions directly, without anyone in between.

Professional interpreters: A trained medical interpreter joins in person, by video or by phone, and interprets between you and an English-speaking clinician.

Translated written materials: Intake forms, consent documents, symptom questionnaires, house rules and discharge instructions are provided in your language.

A bilingual clinician usually allows the most natural conversation. Translated documents matter more than people expect, because consent forms, medication information and the discharge plan are things you will need to reread later, often after the clinician who explained them is no longer in the room.

The Gap Most Families Miss: Group Therapy Hours

Here is the operational detail that changes the picture. A residential treatment day is built mostly around group programming: process groups, skills groups, psychoeducation and community meetings. Individual therapy and psychiatric visits are a smaller share of the week. That means a program can truthfully say “we provide interpreters for individual sessions” while most of a person’s scheduled therapeutic hours still happen in English.

Some people with conversational English do well in English-language groups and only need language support for psychiatric visits, family sessions and consent. Others would sit through every group understanding a fraction of it. The useful question is not “do you have interpreters?” but “how many of my scheduled hours each week will be in a language I fully understand?” Ask the admissions team to answer with a number, even an estimate, and to name which parts of the schedule are covered.

The same logic applies to family sessions. If a parent or spouse who will be part of the support plan at home does not speak English comfortably, ask whether family sessions can be interpreted, because the discharge plan only works if the people carrying it out understand it. Our guide to residential mental health treatment explains how the rest of the week is usually structured.

Why a Family Member Should Not Be the Interpreter

When no interpreter is arranged, the bilingual adult child or spouse often steps in. In a clinical session it usually creates problems.

Filtering: A family member may soften, skip or reword what is said, sometimes to protect the person and sometimes to protect themselves.

Privacy: A person may not disclose trauma, substance use, relationship conflict or thoughts of self-harm with a relative listening.

Accuracy: Clinical terms, medication instructions and diagnostic questions are hard to interpret correctly without training, even for a fluent speaker.

Role strain: The family member stops being a support person and becomes part of the clinical process, during what may already be the hardest stretch of their year.

Family involvement is valuable. It works best when the relative is in the room as family, with a trained interpreter or a bilingual clinician handling the language.

Crisis Lines Offer Language Support Too

Language access matters before and after treatment, not only during it. The 988 Suicide and Crisis Lifeline offers call, text and chat in English and Spanish, and according to SAMHSA, call services with interpreters are available in more than 240 languages (SAMHSA: 988 Frequently Asked Questions, checked October 8, 2026). People can also contact 988 if they are worried about a loved one. That makes 988 one of the few mental health crisis resources in the United States where a person who speaks little or no English can reach a trained crisis counselor at any hour, and it is worth saving in the phone of every family member before treatment begins.

If you or someone you love is thinking about suicide or self-harm, call or text 988 now. If there is immediate danger, call 911 or go to the nearest emergency room. A residential program is not an emergency service and cannot respond to a crisis happening at home.

For non-emergency help finding treatment, SAMHSA’s National Helpline at 1-800-662-4357 is free, confidential and available 24 hours a day, 365 days a year, in English and Spanish (SAMHSA National Helpline).

Insurance and Language Support

Language access also shows up on the insurance side. SAMHSA recommends calling the number on your insurance card to ask what level of care is covered and how many days of treatment are covered per year, and notes that you can ask your plan to authorize a trusted person to speak with them about your coverage (SAMHSA: What Does Health Insurance Cover?). Many health plans also offer interpreter services through member services. If you need one for the coverage call itself, ask for it at the start of the call rather than struggling through the benefits explanation.

If you would like help working out what your plan covers for residential care, you can verify your insurance online or call 877-883-0780.

Six Questions to Ask Before Admission

Write these down before the first call to any residential program. Ask for the answers in writing.

  1. Do you have clinicians on staff who speak my language, and would one of them be my primary therapist or psychiatric provider?
  2. If not, how do you provide interpreters: in person, by video or by phone? Are they trained medical interpreters?
  3. Out of my scheduled therapy hours each week, roughly how many would be in my language or interpreted?
  4. Are the consent forms, medication information and discharge plan available in my language?
  5. Can family sessions be interpreted for relatives who do not speak English comfortably?
  6. If my aftercare therapist or psychiatrist speaks only English, how will the handoff be handled?

The answer to question 3 is often the most revealing. A program that can answer it clearly has thought about the issue. A program that cannot may still be a good fit, but you will know to ask more. You can compare options across levels of care on our treatment programs page.

One Thing to Do Today

Before you call any program, write a short description of what has changed, in your own language and in plain words: how long it has been going on, what a bad day looks like, and what you or your family member has stopped doing. Include any words that do not translate well. Bring that page to the admissions call and to the first assessment. It gives the clinician and interpreter something concrete to work from, and it protects the details that tend to disappear when someone is tired and speaking a second language.

If you are trying to sort out residential options for yourself or someone you love, you can reach our team at 877-883-0780 to talk through programs, insurance and language needs.

This article is for educational purposes only and is not medical advice, diagnosis or treatment. Program services, language access and insurance coverage vary; confirm details directly with the program and your health plan. If you are in crisis, call or text 988 or call 911 in an emergency.


Two people sitting quietly side by side on a wooden bench facing a green lotus pond

For many people with social anxiety disorder, the hardest part of residential mental health treatment is not the therapy itself. It is the schedule around it: meals eaten at a shared table, a roommate, a morning check-in where everyone says how they slept, and several group sessions a day with people they met yesterday. Families often expect the clinical work to be the obstacle. The person going in is usually more worried about lunch.

This guide explains how social anxiety disorder is assessed, why a residential setting feels hardest in the first few days, how treatment is usually paced, and what to ask a program before admission so the plan fits the person rather than the other way around.

What Social Anxiety Disorder Is and How the Diagnosis Is Made

Social anxiety disorder is an anxiety disorder in which a person feels strong fear or anxiety in situations where they might be watched, judged or evaluated by others, and either avoids those situations or gets through them with intense discomfort. According to the National Institute of Mental Health (NIMH), those feelings must last at least 6 months and interfere with daily life, such as work, school or relationships, before a clinician diagnoses the disorder. That 6-month threshold is what separates the disorder from a rough patch of nerves before a new job or a hard semester.

During an assessment, a clinician typically asks when the symptoms began, how long they have lasted, how often they occur and what they have cost the person in work, school or relationships. A physical exam may be part of the process to rule out an unrelated medical cause. NIMH also notes that people with social anxiety disorder are less likely to seek help on their own, and that providers often identify it while treating something else, such as depression. In a residential admission, that is common: the referral says depression or panic, and the social anxiety surfaces during the intake interview.

Social anxiety is not rare or unusual. NIMH reports that about a third of U.S. adolescents and adults experience an anxiety disorder at some point in their lives, and its anxiety disorders overview lists social anxiety disorder among the main types.

Why the First Days of a Residential Stay Feel Hardest

Residential treatment is built around community. That is part of what makes it effective, and it is also exactly what a person with social anxiety has spent years arranging their life to avoid. The friction tends to come from a few predictable places:

  • Shared meals: Eating in front of others is one of the situations NIMH lists as a common trigger, and in residential care it happens several times a day.
  • Group sessions: Being asked to speak, even briefly, in front of a room of new people is the core feared situation for many people with this disorder.
  • Roommates and common areas: There is less private space to retreat to, so the usual escape routes are not available.
  • Being new: Everyone else seems to know the routine, which makes asking simple questions feel exposing.
  • Anticipatory worry: NIMH notes that people with social anxiety may worry about a social situation for weeks before it happens, so the dread of admission often starts well before the first day.

What families often notice in the first week is quiet withdrawal rather than visible distress: short phone calls, a lot of time in the bedroom during free periods, “it’s fine” in answer to every question. That pattern is not a sign that treatment is failing. It is usually the starting point the clinical team is working from.

How Treatment Is Usually Paced

NIMH describes cognitive behavioral therapy (CBT) as the research-supported “gold standard” psychotherapy for social anxiety disorder. CBT helps a person notice and test the predictions that drive the fear, and it includes practicing social skills. Exposure therapy, a CBT method, involves progressively confronting the situations a person has been avoiding, often alongside relaxation exercises. NIMH also notes that CBT delivered in a group format can offer specific benefits for social anxiety, and that acceptance and commitment therapy (ACT) has a growing research base for this disorder.

In a residential setting, the word that matters is “progressively.” A well-run program does not expect someone to share a personal story in their first group. A more typical progression looks like this:

  • Sitting in group without being required to speak for the first few sessions
  • Answering a structured check-in question, such as rating mood from 1 to 10
  • Asking staff one practical question a day
  • Making a brief contribution in group, then a longer one
  • Practicing a feared situation that matters outside treatment, such as a phone call or a short conversation with a stranger, with the therapist planning it in advance

The milieu itself becomes part of the exposure work. The hard part for families and patients to hear is this: most residential schedules cannot be built around avoiding groups, so the realistic request is pacing, not an exemption. A program that offers to excuse someone from all group sessions may be making the stay more comfortable while removing the very practice that helps.

Medication may also be considered. Decisions about whether to use medication, and which kind, are made individually with a prescribing clinician, and NIMH notes that both therapy and medication can take some time to work.

Conditions That Often Come With It

According to NIMH, people with social anxiety disorder may also have depression, other anxiety disorders, obsessive-compulsive disorder, ADHD, body dysmorphic disorder or bipolar disorder, and the disorder is commonly associated with alcohol and substance misuse. Many people use alcohol to get through social situations, and that pattern can become its own problem. When more than one condition is present, a comprehensive plan that addresses all of them matters more than treating the most visible symptom.

Questions to Ask a Program Before Admission

Here is one thing you can do today: ask the program to send its actual weekly schedule, then count the hours of group sessions and the number of individual therapy sessions. That one document tells you more about fit than any brochure. Then ask:

  • How many individual therapy sessions per week are included, and who provides them?
  • Is CBT or exposure-based work part of the plan for social anxiety specifically, or is it general group therapy only?
  • How is participation in group paced for someone with social anxiety during the first week?
  • Are rooms shared, and is there a quiet space during free time?
  • How is co-occurring alcohol or substance use assessed and treated?
  • How will family members be updated, and how often?
  • What does the discharge plan include for continuing exposure work at home?

Before the call, it also helps for the person to write down the three social situations they avoid most and how long they have been avoiding them. That list gives the intake clinician a concrete starting point and helps the team set early goals.

If you would like help comparing programs, call 877-883-0780. You can also read more about residential mental health treatment or review the full range of treatment programs.

When Residential Care Is and Is Not the Right Level

Many people with social anxiety disorder do well in outpatient therapy. Residential treatment tends to come up when avoidance has narrowed life significantly, when depression or substance use has developed alongside the anxiety, or when outpatient care has not been enough. A clinical assessment, not the label on the diagnosis, should decide the level of care. If cost is a concern, you can verify your insurance benefits before making any decision.

If Things Feel Urgent

Social anxiety disorder often travels with depression. If you or someone you love is having thoughts of suicide, call or text 988 to reach the 988 Suicide and Crisis Lifeline, available 24 hours a day. If anyone is in immediate danger, call 911 or go to the nearest emergency room. Residential treatment programs are not emergency services. For treatment referrals, SAMHSA’s National Helpline (1-800-662-4357) is free, confidential and available 24/7.

Taking the First Step

The fear of walking into a room full of strangers is the symptom, not a reason to stay home. Good programs expect it, plan for it and pace the work so that the first week is manageable and the following weeks build real confidence. To talk through options for yourself or a family member, call 877-883-0780.

This article is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Treatment decisions, including any decisions about medication, should be made with a qualified health care provider. Clinical details were checked against NIMH sources on October 8, 2026. If you are experiencing a mental health emergency, call or text 988 or call 911.

A closed laptop resting on a wooden table in soft warm light, representing stepping away from work for mental health treatment

For many working adults, the question that delays residential mental health treatment is not whether they need it. It is what happens to their job while they are gone. This post walks through the practical side of taking time off work for residential mental health care, from the first email to HR to the first week back.

Nothing here is legal advice. Leave rights depend on your employer, your job and your state, so treat this as a guide to the questions to ask, not a ruling on your situation.

Why Work Is Often the Real Barrier

Many adults who could benefit from mental health care do not receive it. According to the National Institute of Mental Health, which reports data from SAMHSA’s 2022 National Survey on Drug Use and Health, an estimated 59.3 million U.S. adults had a mental illness in 2022, and 50.6% of them received mental health treatment in the past year. That leaves roughly half without treatment. For an adult considering residential care, worry about work is one practical barrier that can usually be handled with a plan: in most workplaces, taking medical leave involves a short written notice to HR, a certification form completed by the treating provider, and an estimated return date that can be updated as treatment goes on.

People in this position often describe the same loop. They know their depression, anxiety or panic symptoms are getting worse. They also know their manager is counting on them for a deadline next month. So they wait for a quieter time at work, and the quieter time does not come. Breaking that loop usually starts with learning that the leave process is more routine, and more private, than it looks from the outside.

What You Actually Have to Tell Your Employer

You generally do not have to tell your manager or coworkers your diagnosis. In most workplaces, the conversation with your direct supervisor can be as simple as: “I need to take medical leave starting on this date. HR has the details.” The medical information goes on a certification form completed by a health care provider, and that form typically goes to HR or a leave administrator rather than to your manager.

Several layers of protection may apply, depending on where you work:

  • Federal job-protected leave: the Family and Medical Leave Act (FMLA) can protect the jobs of eligible employees who need time off for a serious health condition, and a stay in a residential care facility may qualify.
  • California job-protected leave: the California Family Rights Act (CFRA) offers similar protection to eligible California employees, and it covers more small employers than federal law does.
  • Partial wage replacement: California State Disability Insurance (SDI) may replace part of your wages if you are unable to work because of a medical condition, including a mental health condition, and you meet the program’s requirements.
  • Workplace accommodations: disability laws may require your employer to consider reasonable adjustments when you return, such as a modified schedule.

Eligibility for each depends on factors such as how long you have worked there, how many hours you have worked and how many people your employer employs. HR, your employee handbook or the agency that runs each program can confirm what applies to you. If you are unsure where to start, our team can talk through timing and program options with you at 877-883-0780.

The Paperwork, Step by Step

Here is a sequence you can start today, even before you have an admission date:

  1. Email HR, not just your manager. One sentence is enough: “I need to request medical leave starting on or around [date]. Please send me the forms and tell me who the treating provider should return them to.” A written request creates a clear record of when you asked.
  2. Ask three specific questions. Which leave programs am I eligible for? Will my health insurance continue during leave, and how will I pay my share of the premium? Do I need to use paid time off first?
  3. Find out the deadline on the form. Certification forms often have a return deadline. Write it down and share it with the admissions team so the clinical team knows when it is due.
  4. Separate the forms. Employer leave forms, state disability claims and any short-term disability policy through your job are usually separate processes with separate forms. Ask HR which ones apply.
  5. Bring copies with you. Pack the blank forms, or have them emailed to an address you can access, so the treatment team can complete their part after the admission assessment.

Before admission, it is also worth confirming coverage for the stay itself. You can verify your insurance benefits online or by phone, which usually happens in parallel with the leave paperwork.

Why the Return Date on the Form Is an Estimate

Almost every leave form asks for an expected return-to-work date. This is the field that causes the most anxiety, because it is the one thing no one can answer precisely before treatment starts. Several factors shape it:

Clinical progress: length of stay in residential mental health treatment depends on how symptoms respond, not on a fixed calendar.

Insurance reviews: many insurers authorize residential care in blocks and review it periodically, so the covered length of stay may not be known at admission.

Step-down planning: some people move from residential care into a lower level of care, such as an outpatient program, which can allow a part-time or phased return.

Medication adjustments: if medication is started or changed, the care team may want time to see how it is working before you return to a full workload.

The practical takeaway: ask the treating provider to give an estimated date or a range, and ask HR how to submit an updated date if the estimate changes. Extending leave is a routine request in most HR departments. Being surprised by the need to extend it is what causes stress.

What the First Week Back Can Look Like

People returning to work after residential care often say the first few days are harder than they expected. The commute feels long. The inbox feels enormous. A coworker asks, kindly, “Where have you been?” and there is a moment of not knowing what to say.

A few things tend to help:

  • A prepared answer. Something short and true, like “I was out on medical leave and I’m glad to be back,” is enough. You do not owe anyone more detail.
  • A first-week check-in with your manager. Agree on priorities for the first two weeks so you are not trying to clear the whole backlog at once.
  • Appointments already on the calendar. Ongoing therapy and psychiatric follow-up should be scheduled before your first day back, with any needed time off requested in advance.
  • A written plan for hard days. Your discharge plan should include early warning signs and who to call. Keep it somewhere you can reach during the workday.

If a phased return or schedule change would help, ask the care team whether they can document that recommendation. HR may need it in writing to consider an accommodation.

Questions to Ask Before Admission

When you speak with a program’s admissions team, it helps to ask about work directly:

  • Who on the team completes employer leave forms and state disability paperwork, and how long does that usually take?
  • Can I have limited phone or email time to handle urgent work or benefits questions during the stay?
  • How will you help me plan the return to work as part of discharge planning?
  • If I step down to outpatient care, can the schedule fit around a part-time return?

For a confidential conversation about timing, call 877-883-0780.

If Things Feel Urgent

Planning leave is for situations where there is time to plan. If you are having thoughts of suicide or are in crisis, call or text 988 to reach the 988 Suicide and Crisis Lifeline, available 24 hours a day. If you or someone else is in immediate danger, call 911 or go to the nearest emergency room. Residential treatment programs are not emergency services. Your job can wait while you get safe.

For help finding treatment options more generally, SAMHSA’s National Helpline (1-800-662-4357) is a free, confidential, 24/7 treatment referral and information service, and the NIMH Find Help page lists additional resources.

A Note on Timing

There is rarely a perfect moment to step away from work. Untreated depression, anxiety, bipolar disorder, PTSD and OCD tend to affect work anyway, and planned leave with a return plan is often less disruptive than pushing through until something forces a stop.

This article is for educational purposes only and is not medical, legal or financial advice. Leave eligibility and benefits vary by employer, state and individual circumstances; confirm details with your employer, the relevant government program or a qualified professional. If you are experiencing a mental health emergency, call or text 988 or call 911.

A person sitting alone on a wooden bench on a grassy hill, looking out over a wide valley under a clear evening sky

When a family member is admitted to residential care for post-traumatic stress disorder (PTSD), one of the first questions families ask is a practical one: will they be made to talk about the worst thing that ever happened to them on the first day? The short answer is usually no. Trauma-focused therapy follows a sequence, and knowing that sequence makes it easier to judge whether a program is a good fit, what the first week is likely to feel like, and what needs to be in place before discharge.

This guide walks through how trauma-focused therapy is typically structured in a residential setting, how long it generally takes, and the specific questions worth asking before and during admission.

The Timeframe Most Families Do Not Expect

According to the National Institute of Mental Health, psychotherapy for PTSD usually lasts 6 to 12 weeks but can last longer, and it can take place one on one or in a group setting. NIMH also notes that if symptoms have not improved after 6 to 8 weeks of treatment, it is reasonable to raise that with the treating provider. Because many residential stays are measured in weeks rather than months, trauma-focused therapy that begins during a residential stay often has to continue in a lower level of care after discharge, so the step-down plan is part of the treatment rather than an afterthought. (Source: NIMH, Post-Traumatic Stress Disorder.)

That last point is the one that catches families off guard most often on placement calls. A stay can end at a point where the person is safer, sleeping better and more stable, but still partway through the trauma work itself. That is not a failure of treatment. It is how the timeline usually fits together, and planning for it early prevents a gap in care at the moment it matters most.

How a Diagnosis Is Confirmed Before Trauma Work Starts

Trauma-focused therapy is designed for a specific diagnosis, so the clinical team first confirms that PTSD is what is going on. NIMH describes the diagnostic threshold this way: an adult must have the required symptoms for at least 1 month, the symptoms must be severe enough to interfere with daily life such as work or relationships, and they must not be better explained by medication, substance use or another illness. Symptoms usually begin within 3 months of the traumatic event, but they can emerge later.

NIMH also notes that people with PTSD often have co-occurring conditions such as depression, substance use or anxiety disorders. In practice, this is why the admission assessment matters so much. If severe depression or unstable sleep is driving most of the day-to-day distress, the team may address that first so the person has enough capacity to do trauma work safely.

Why Trauma Therapy Is Sequenced Instead of Started on Day One

Residential programs generally build trauma treatment in stages. The reasons are practical and clinical:

  • Stabilization comes first: a person who is not sleeping, is in acute distress or has recently been in crisis usually needs those issues addressed before deliberately revisiting traumatic memories.
  • Skills before exposure: grounding and distress-tolerance skills give the person tools to use when therapy stirs up strong reactions between sessions.
  • Trust with the therapist: trauma work depends on feeling safe with the person guiding it, and that relationship takes some time to build.
  • Avoiding retraumatization: pushing into detailed trauma content too fast can increase distress rather than reduce it, which is why trauma-informed programs pace the work deliberately.

The Substance Abuse and Mental Health Services Administration describes a trauma-informed approach as one built around safety, trust, collaboration and empowerment, and one that actively seeks to resist retraumatization (SAMHSA, Trauma-Informed Approaches and Programs). A program that can explain how it applies those principles to its own schedule is giving you a useful signal.

What a Trauma-Focused Session Usually Looks Like

NIMH identifies cognitive behavioral therapy as a common type of psychotherapy for PTSD and describes two components it can include. Programs use different named protocols, but most sessions draw on one or both of these:

Exposure therapy: The goal is to reduce the hold that fear has by approaching the trauma gradually and in a safe, structured way. Depending on the approach, the person may talk or write about the event, or gradually approach places or situations they have been avoiding. The pace is planned with the therapist, not imposed. A session often begins with a check-in on how the person has been since the last meeting, moves into the planned exposure work, and ends with time to settle and review before returning to the rest of the day.

Cognitive restructuring: This part focuses on how the person makes sense of what happened. Many people carry guilt or shame about things that were not their fault, or remember the event in a way that keeps them stuck. The therapist helps them examine those beliefs and arrive at a more realistic understanding. This often involves written worksheets or practice assignments between sessions.

In a residential setting, those individual sessions are typically surrounded by other parts of the day: group sessions on skills, time with the psychiatric provider, and structured routines around meals and sleep. Medication can be part of the plan as well. NIMH notes that some medications are FDA-approved for PTSD and may be prescribed alongside psychotherapy; decisions about any specific medication are made with the prescribing provider.

What the First Weeks Tend to Feel Like

Families sometimes notice something that seems backward: a loved one may sound more upset on phone calls after trauma work starts than they did during the first few days. Approaching avoided memories is hard, and a temporary rise in distress early in exposure-based work is something clinicians watch for and plan around. What matters is whether the team is tracking it, whether the person has skills to use, and whether the overall direction over several weeks is toward fewer symptoms and less avoidance.

Other changes people often describe are quieter. Sleep may become more regular once routines settle. Someone who would not drive past a certain street may start talking about it. Conversations may shift from what happened to what they want to do next. None of these happen on a fixed schedule, and progress is rarely a straight line.

Questions to Ask Before and During Admission

You can use this list on your next call with a program or at the next family session. Write the answers down so you can compare programs or track changes over time.

  1. Which trauma-focused therapy approaches do your clinicians use, and are the therapists who deliver them trained in those specific methods?
  2. When does structured trauma work usually begin, and what has to be in place first?
  3. How many individual trauma-focused sessions are scheduled per week?
  4. How do you measure whether PTSD symptoms are improving, and how often is that reviewed?
  5. What happens if symptoms have not improved after 6 to 8 weeks?
  6. If the stay ends before the therapy is finished, who continues the trauma work after discharge, and will they use the same approach?
  7. How are co-occurring depression, anxiety or substance use addressed alongside PTSD?

Question 6 is the one to push on. A strong answer names a level of care, such as outpatient or intensive outpatient treatment, and explains how the treatment record and progress are handed off. If the answer is vague, ask the program to put the step-down plan in writing before discharge.

If you are still weighing whether a residential setting is the right fit, our overview of residential mental health treatment explains what that level of care includes. To understand what your plan may cover before you call, you can verify your insurance online or speak with our team at 877-883-0780.

If Someone Is in Crisis Right Now

Trauma symptoms can sometimes come with thoughts of suicide or self-harm. If you or someone you love is having those thoughts, call or text the 988 Suicide and Crisis Lifeline by dialing 988, available 24 hours a day. If someone is in immediate danger, call 911 or go to the nearest emergency room. Residential treatment programs are not emergency services and cannot respond to a crisis in progress.

Getting Started

PTSD is treatable, and trauma-focused therapy is one of the main ways it is treated. The most useful thing families can do is understand the sequence, ask direct questions about timing and continuity, and make sure the plan extends past the last day of a residential stay. If you would like help finding a program that fits your situation, call 877-883-0780 to talk through your options.

This article is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Always seek the advice of a qualified mental health professional or other health care provider with any questions about a medical condition or treatment, including any medication decisions.

Soft daylight through a bedroom window framing autumn trees with orange and green leaves

Many people feel slower and flatter when the days get shorter. For some, that seasonal dip is a recognized form of depression called seasonal affective disorder, or SAD. The difference between the two matters, because it changes what gets assessed and what treatment looks like. This article walks through how a clinician decides whether a seasonal pattern is present, what light therapy and other treatments actually involve, and what you can track now, before the clocks change, so the conversation with a care team starts with real information.

How Seasonal Affective Disorder Is Diagnosed

Seasonal affective disorder (SAD) is diagnosed by pattern, not by a single hard winter. According to the National Institute of Mental Health, a person must have depressive episodes that occur during a specific season for at least 2 consecutive years, and those seasonal episodes must be more frequent than depressive episodes at other times of the year. In most cases symptoms start in late fall or early winter, ease in spring and summer, and last about 4 to 5 months of the year.

That two-year requirement is why a diagnosis often cannot be made from how someone feels this month alone. A clinician will usually ask about past years, may use a questionnaire, and will look for the symptoms of depression plus the features that often go with the winter pattern: oversleeping, overeating with carbohydrate cravings and weight gain, and pulling away from people. A less common summer pattern looks different, with trouble sleeping, poor appetite, restlessness and anxiety. The NIMH overview of seasonal affective disorder lays out these criteria in plain language.

It also helps to know what SAD is not. NIMH notes that it is tied to changes in daylight, not the calendar. Stress around the holidays, family visits or a busy season at work can make anyone feel worse, but that is not the same condition.

What Researchers Think Drives the Winter Pattern

Researchers are still working out the causes, and most of the evidence so far is about the winter pattern. The leading explanations, as summarized by NIMH, are:

  • Reduced serotonin activity: Shorter daylight hours appear to interfere with molecules that help keep serotonin, a brain chemical involved in mood, at normal levels.
  • Too much melatonin: People with winter-pattern SAD may produce excess melatonin, the hormone that regulates sleep, which can add to sleepiness and oversleeping.
  • Lower vitamin D: Less sunlight on the skin can mean lower vitamin D, which is believed to support serotonin activity.
  • A body clock that cannot adjust: Together, these shifts can leave the daily sleep-wake rhythm out of step with the season, which shows up as changes in sleep, mood and behavior.

NIMH also points out that SAD is more common in women, usually begins in young adulthood, and is more common in people who live farther north. Living in California lowers the odds compared with Alaska or New England, but it does not rule SAD out. The diagnosis rests on the pattern, not the zip code.

What Light Therapy Actually Involves

Light therapy has been a mainstay for winter-pattern SAD since the 1980s. In the form NIMH describes, a person sits in front of a light box rated at 10,000 lux for about 30 to 45 minutes each day, usually first thing in the morning, from fall to spring. These boxes are roughly 20 times brighter than ordinary indoor light and filter out ultraviolet light.

A few practical points tend to get missed:

  • It is a daily routine across months, not a one-time fix, so the morning schedule has to make room for it.
  • People with certain eye conditions, or who take medications that increase sensitivity to light, may need a different approach or medical supervision. That is a reason to bring a complete medication list to the appointment where light therapy comes up.
  • Light therapy is a treatment for the winter pattern. NIMH notes there are no treatments specific to the summer pattern.

Other Treatments and How Long They Take

NIMH groups SAD treatment into four categories that can be used alone or together: light therapy, psychotherapy, antidepressant medication and vitamin D.

Psychotherapy. Cognitive behavioral therapy has been adapted for SAD. The version NIMH describes runs as two weekly group sessions for 6 weeks. It focuses on reworking negative thoughts about the season and on behavioral activation, which means planning engaging activities on purpose to offset the pull toward withdrawal. In head-to-head research summarized by NIMH, it worked about as well as light therapy, and its benefits appeared to last longer.

Medication. Antidepressants can help with SAD, alone or alongside therapy. NIMH notes they usually take 4 to 8 weeks to work, and that sleep, appetite and concentration often improve before mood does. Which medication, if any, is a decision for a prescriber who knows the full history. Do not start, stop or change a medication on your own.

Vitamin D. Studies of vitamin D for SAD have produced mixed results. Ask a clinician before relying on it.

The Two-Winter Check You Can Do This Week

Because the diagnosis depends on at least two years of history, the most useful thing you can bring to an appointment is a rough timeline. In California, clocks fall back at 2 a.m. on Sunday, November 1, 2026, and do not spring forward until Sunday, March 14, 2027. That is 19 weeks of earlier evenings. Before then, take 20 minutes and do this:

  1. Open your phone calendar, photos or messages for October through March of the last two winters.
  2. Note roughly when you started sleeping more, canceling plans, eating differently or missing work, and when that lifted.
  3. Write down anything you tried and whether it helped.
  4. Ask one person who sees you often whether they noticed the same timing.
  5. Bring the page to your next appointment and ask directly: “Does this look like a seasonal pattern, and would that change what you recommend?”

Families often see the pattern before the person living it does. The same partner or parent who notices withdrawal every January can add dates that someone in the middle of a depressive episode may not remember clearly.

Why Seasonal Depression and Bipolar Disorder Are Checked Together

NIMH notes that SAD is more common in people with bipolar disorder, especially bipolar II, which involves depressive episodes alternating with hypomanic episodes. In practice, that means a clinician who hears “I crash every winter” will usually also ask what happens in spring. A lift that feels like more than relief, such as needing much less sleep, racing thoughts or unusual spending, is important to mention. It can change the treatment plan, so share it even if it felt good at the time.

When Seasonal Depression Needs More Than Outpatient Care

Most people with SAD are treated in outpatient settings. A higher level of care may be worth discussing when depression has stopped someone from working or caring for themselves, when outpatient treatment has not helped, or when SAD sits alongside another condition such as an anxiety disorder, panic disorder or bipolar disorder. A residential mental health program provides daily structure, therapy and psychiatric care in one place, and a seasonal history gathered in advance helps the team plan from day one. You can compare levels of care on our treatment programs page or verify your insurance before you call. To talk through options, call 877-883-0780.

If Things Feel Urgent

Thoughts of death or suicide can be part of any depression, including seasonal depression. If you or someone you love is having thoughts of suicide or is in emotional crisis, call or text the 988 Suicide and Crisis Lifeline at 988, available 24 hours a day. SAMHSA explains how the 988 Lifeline works. If anyone is in immediate danger, call 911 or go to the nearest emergency room. Residential treatment programs are not emergency services.

Getting Started

A seasonal pattern is a real, treatable form of depression, and it is easier to treat when the history is clear. If you are noticing the same slide each fall and want to talk through what kind of care fits, call 877-883-0780. For a broader look at depression symptoms and treatment, see NIMH’s depression overview.

This article is for educational purposes only and is not medical advice, a diagnosis or a substitute for evaluation by a qualified health care professional. Decisions about diagnosis, light therapy and medication should be made with a licensed clinician. Do not start, stop or change any medication without talking to your prescriber.

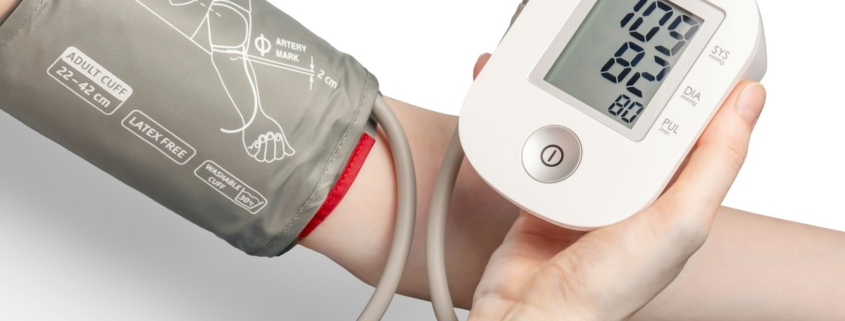
A blood pressure cuff on an adult arm with a digital monitor held in one hand, part of a routine physical exam

Before a psychiatric team settles on a diagnosis of depression or an anxiety disorder, someone has to ask a plain medical question: could something else in the body be producing these symptoms? Fatigue, poor sleep, a racing heart, low mood and trouble concentrating can come from a mental health condition. They can also come from a thyroid problem, a lingering infection, a medication side effect or a change in substance use. This article walks through how that medical check usually works, what gets ordered, and what you can gather in advance so it does not slow down care.

Why a Medical Rule-Out Comes Before the Diagnosis

The National Institute of Mental Health states that certain medications and medical conditions, such as viruses or thyroid disorders, can cause the same symptoms as depression, and that a provider can rule out these possibilities through a physical exam, an interview and lab tests. NIMH also notes that a depression diagnosis requires symptoms most of the day, nearly every day, for at least 2 weeks, while generalized anxiety disorder requires difficulty controlling worry on most days for at least 6 months. Those time thresholds, checked at the NIMH source pages on October 6, 2026, are why a clinician asks how long symptoms have lasted and whether anything medical changed around the time they started. You can read the full descriptions in NIMH’s depression publication and its generalized anxiety disorder publication.

None of this means the symptoms are “not real” if a medical cause turns up. It means treatment is aimed at the right target. And very often, the medical workup comes back unremarkable, which is useful information in its own right: it lets the team focus on psychiatric care with more confidence.

What the Physical Exam and Interview Cover

The medical part of a mental health evaluation is usually less dramatic than people expect. It tends to include vital signs, a general physical exam and a detailed history. The history matters most. A clinician will typically ask:

  • When the symptoms began, and whether anything changed around that time: a new diagnosis, a new prescription, a dose change, an illness, a pregnancy or postpartum period, or a shift in alcohol or drug use.
  • Whether there is a personal or family history of thyroid disease, diabetes, heart problems, seizures or other chronic conditions.
  • What every current medication and supplement is, including over-the-counter products, since some can affect mood, sleep or energy.
  • How much caffeine, alcohol and nicotine are part of a typical day, since all three can affect anxiety and sleep.
  • Whether there have been physical symptoms such as weight change, heat or cold intolerance, chest pain, fainting or unusual headaches.

Answering these honestly is not a test. Clinicians ask the same questions of everyone because the answers change what the next step should be.

Lab Work That Is Commonly Ordered

There is no single blood test that diagnoses depression or an anxiety disorder. Lab work is used to look for other explanations. Exactly what gets ordered depends on age, history and symptoms, and the decision belongs to the treating clinician. Commonly ordered tests may include a complete blood count, a basic or comprehensive metabolic panel, and thyroid function tests. Depending on the history, a clinician may also check certain vitamin levels, screen for substances, or order a pregnancy test. If a medication that needs blood-level or organ-function monitoring is being considered, baseline labs may be drawn before it is started.

Results that come back outside the normal range do not automatically explain the symptoms. A mildly abnormal value may be followed up, repeated or simply noted. That interpretation is a conversation to have with the prescriber, not something to work out from a portal message at midnight.

Common Reasons a Medical Cause Gets a Closer Look

Clinicians tend to look harder for a medical contributor in a few recognizable situations:

New symptoms later in life: A first episode of depression or significant anxiety that begins in middle or later adulthood, with no earlier history, prompts a more careful medical check.

A recent medication change: Symptoms that start soon after a new prescription or dose change raise the question of a side effect, which only the prescriber should evaluate.

Physical symptoms that do not fit: Unexplained weight change, persistent fevers, chest pain or neurological changes point toward a medical workup alongside psychiatric care.

A change in substance use: Starting, increasing or stopping alcohol or other substances can produce anxiety, low mood and sleep disruption on its own.

Treatment that is not working as expected: When symptoms do not respond as anticipated, a team may revisit whether a medical factor was missed.

How This Works Before Residential Treatment

When someone is being considered for residential mental health treatment, the program needs to know whether it can safely meet that person’s medical needs on site. A residential mental health program is not a hospital. That is why admissions teams commonly ask for recent medical records, a current medication list and, in some cases, recent lab results before or shortly after admission. If an urgent medical issue is uncovered, it generally has to be addressed first.

Here is an operational detail that slows people down more often than any clinical question: lab results ordered by a primary care office are usually sent back to that office and to the patient’s portal, not to the treatment program. The program cannot act on a result it has never received. Asking the primary care office to send results and visit notes directly to the admitting program, and confirming they arrived, often saves days. Our admissions team can help coordinate this at 877-883-0780.

Insurance can also shape timing. Some plans want documentation before authorizing a residential stay. If you are not sure what your plan requires, you can verify your insurance benefits before the first call so that paperwork is not the bottleneck.

What to Gather This Week

You can do most of the groundwork yourself, today, without waiting for anyone. Here is a short checklist:

  1. Request your most recent labs and visit notes. Call your primary care office or log in to your patient portal and download or request results from the past 12 months. Ask the office how to send them directly to another provider.
  2. Write down your medication list. Include every prescription, over-the-counter product and supplement, the dose, who prescribed it and roughly when it started. Bring the original labeled containers if you are admitting to a program.
  3. Note the timeline. On one page, write when the symptoms began and anything that changed in the months before: illnesses, prescriptions, life events, alcohol or substance use.
  4. Ask one direct question at your next appointment: “Has anything medical been ruled out for these symptoms, and is there any lab work you would want before treatment starts?”

That last question is worth asking even if you have been in mental health care for years. Records get split across providers, and a test that “someone probably ran” may never have been ordered.

What Families Notice and Can Share

Family members often see things the person in treatment does not mention. A partner may notice that the low mood started around the time a new prescription was filled. A parent may remember that a sibling or grandparent had thyroid disease. An adult child may have watched a parent’s drinking change over the past year. With the person’s written permission, these observations can be shared with the care team. If you are not sure what can be discussed, ask the program how it handles releases of information.

When Symptoms Are Urgent

A medical rule-out is part of planned care. It is not a reason to wait if someone is in danger. If you or someone you love is having thoughts of suicide or is in emotional crisis, call or text the 988 Suicide and Crisis Lifeline at 988, available 24 hours a day. SAMHSA explains how the 988 Lifeline works. If anyone is in immediate danger, or has symptoms such as chest pain, fainting or sudden confusion, call 911 or go to the nearest emergency room. Residential treatment programs are not emergency services.

Getting Started

Ruling out medical causes is a normal, often reassuring part of getting the right mental health care. It works best when records move quickly and the history is complete. If you are considering residential care for depression, anxiety, bipolar disorder, PTSD, OCD or panic disorder, you can review our treatment programs or call 877-883-0780 to talk through what records to gather and what the next step looks like.

This article is for educational purposes only and is not medical advice, a diagnosis or a substitute for evaluation by a qualified health care professional. Decisions about testing, diagnosis and medication should be made with a licensed clinician. Do not start, stop or change any medication without talking to your prescriber.

A woman in a red coat talking on her phone beside a calm lake in soft evening light

Most people who call about residential mental health care are not calling on a calm afternoon with a list of questions. They are calling after a week of a family member not sleeping, or after an outpatient therapist said the words “a higher level of care,” or after a long night of searching and getting nowhere. What they want to know first is simple: what actually happens on this call, and what am I agreeing to by making it?

This article walks through how a care navigation call works at Bodhi Mental Health, what gets checked, what does not get decided for you, and what to have in front of you before you dial. It is written in procedural terms on purpose, because the logistics are where families most often get stuck.

What a care navigation service is, and what it is not

Bodhi Mental Health is a care navigation and referral service based in Capitola, California, not a treatment provider: the residential, outpatient and virtual programs it helps families compare are operated independently, and treatment is delivered by those programs. As of October 6, 2026, the Bodhi site lists five plans it does not take: Medi-Cal, Medicare, Medicaid, Ambetter and IEHP. A person covered only by one of those plans will usually move faster by calling the behavioral health number on their insurance card or their county behavioral health services directly, rather than starting with a navigation call that cannot use that coverage.

That distinction matters more than it sounds. A navigation service can listen, explain levels of care, check insurance benefits and introduce you to programs that may fit. It cannot admit you, diagnose you, prescribe anything or promise a bed. The admitting program makes those decisions after its own clinical assessment, and you connect with that program directly.

What happens on the first call

The structure Bodhi describes on its own site has three parts: listen, clarify and connect. In practice, a first call usually sounds like this.

Listen: You describe what is going on in your own words, including who the care is for, what has already been tried and what feels most urgent right now.

Clarify: The navigator helps sort out which level of care the situation may point toward, such as residential treatment, a partial hospitalization program, intensive outpatient care or virtual care, and walks through what your insurance may cover.

Connect: If there is a reasonable match, you are introduced to one or more independent programs, and from there the conversation about admission happens between you and that program.

For many families, the hardest part is not the call itself but the minute before it, when they were not sure whether their situation was “serious enough.” There is no threshold you need to prove on a navigation call. Describing what you have seen, plainly, is enough to start.

What the insurance check actually looks at

An insurance verification is a benefits check, not a guarantee of payment. It typically confirms whether your plan includes mental health benefits for the level of care being discussed, whether a program is in network or out of network, and what your deductible and out-of-pocket maximum look like for the plan year. You can start one through the verify insurance page or by phone.

A few points cause confusion repeatedly, so it helps to know them in advance.

Prior authorization: Many plans require approval before a residential stay begins, and the program usually submits that request after its own assessment, not the navigation service.

Approved days: When a plan authorizes residential care, it may approve a set number of days and then review progress before approving more, so the length of a stay is not always known on day one.

Network status: An out-of-network program is not automatically unaffordable, but costs and reimbursement rules usually differ from in-network care, and those differences should be in writing before admission.

Plan type: PPO, HMO, union, government employee and federal employee plans each have their own rules about referrals and networks, which is why the plan type is one of the first questions asked.

The Substance Abuse and Mental Health Services Administration publishes plain-language guidance on understanding what your insurance covers for mental health care, and it is worth reading before any benefits conversation.

What to have in front of you before you call

You can do this today, even if you are not ready to call yet. Gather these items and keep them in one place.

  • The front and back of the insurance card for the person who needs care, including the member ID and the behavioral health or mental health phone number printed on the back.
  • The name and date of birth of the policyholder, if that is a different person.
  • A short list of current medications and prescribers. Names are enough for a first call; you do not need doses memorized.
  • Any treatment already tried in the last year, such as therapy, an outpatient program, a hospital visit or a crisis evaluation, with rough dates.
  • Two or three sentences describing what has changed recently. Writing them down keeps the call focused when emotions run high.

One more step that saves time: call the behavioral health number on the back of the card yourself and ask, word for word, “Does my plan require prior authorization for residential mental health treatment, and do I have any out-of-network benefits?” Write down the answer, the date and the name of the representative. That single note answers two of the questions every program will ask.

What stays your decision

A navigation call does not commit you to anything. You choose whether to speak with a program, whether to tour it, whether to proceed with its assessment and whether to accept an admission offer. The National Institute of Mental Health offers a general overview of how to find help and what to look for in mental health care, which can be a useful companion while you compare options.

When a program is suggested, these are reasonable questions to ask the program itself before admission:

  • What is your state license or certification, which agency issued it, and how can I look it up?
  • Who provides psychiatric oversight, and how often does a psychiatrist or psychiatric nurse practitioner see residents?
  • What conditions do you treat as a primary focus, and which do you refer elsewhere?
  • What will I owe out of pocket if insurance authorizes fewer days than expected?
  • What does discharge planning look like, and when does it start?

A program that answers these clearly, in writing where money is involved, is giving you the information you need to decide. Our treatment programs page outlines the levels of care families most often compare.

When a navigation call is the wrong first step

A care navigation line is not an emergency service, and it is not built for a crisis happening right now. If you or someone you love is thinking about suicide, is talking about not wanting to be alive, or is in emotional distress that feels unmanageable, call or text the 988 Suicide and Crisis Lifeline, available 24 hours a day. If anyone is in immediate danger, call 911 or go to the nearest emergency department. Residential programs are designed for planned admissions after an assessment, not for emergency stabilization.

Once immediate safety is addressed, a navigation call can help with what comes next, including step-down planning after an emergency visit or a short hospital stay.

Making the call

If you have your insurance card and a few notes ready, the first call usually covers more ground than people expect. You can reach the Bodhi team at 877-883-0780 for a free, confidential conversation about levels of care, insurance and which independent programs may fit. If you are calling on behalf of an adult child, a partner or an employee, say so at the start; the questions are slightly different, and the navigator can adjust.

If you are not ready to talk yet, that is fine too. Gathering the items above is real progress, and the number will be the same when you are ready: 877-883-0780.

This article is for educational purposes only and is not medical, psychiatric, insurance or legal advice. Bodhi Mental Health provides care navigation and referrals; treatment is provided by independent programs, which make their own clinical and admission decisions. Insurance benefits, authorization rules and program availability vary by plan and program, so confirm details directly with your insurer and any program you consider. If you are in crisis, call or text 988, or call 911 in an emergency.

A fenced gravel path leading toward misty mountains at sunrise

Families often ask a version of the same question a week or two into a residential stay: “Is it working?” Staff can describe how someone seems in groups, but many programs also track progress with short, standardized questionnaires. The two most common for adults are the PHQ-9 for depression and the GAD-7 for anxiety. Knowing how these tools are built, how often they are given and what the numbers can and cannot tell you makes it much easier to ask the care team useful questions.

This guide explains how measurement-based care usually works in residential mental health treatment, using the scoring rules published by the Centers for Disease Control and Prevention. If you want to talk through a specific situation, you can reach our admissions team at 877-883-0780.

What the PHQ-9 and GAD-7 Actually Measure

The PHQ-9 and GAD-7 are short self-report questionnaires that score how often depression and anxiety symptoms occurred over the past 2 weeks. On the PHQ-9, each of 9 items is scored 0 to 3, for a total of 0 to 27, and the CDC uses a score of 10 or higher as its well-validated cut point for depression. On the GAD-7, 7 items produce a total of 0 to 21, with 0 to 4 read as minimal, 5 to 9 as mild, 10 to 14 as moderate and 15 to 21 as severe anxiety symptoms. Neither score is a diagnosis on its own; a clinician interprets it alongside an interview and history.

Those scoring rules come from two National Center for Health Statistics reports: a February 2018 CDC data brief on depression prevalence, which describes the PHQ-9 as a nine-item instrument covering the past 2 weeks, and a September 2020 CDC data brief on anxiety symptoms, which lays out the GAD-7 severity bands. Both questionnaires use the same four answer choices: “not at all,” “several days,” “more than half the days” and “nearly every day.”

For background on the symptoms these tools ask about, the National Institute of Mental Health’s depression overview is a reliable, plain-language starting point.

How the Measures Are Usually Used During a Stay

Programs vary, so treat the following as a typical pattern rather than a rule. Ask your program how it does things.

  • At admission. A baseline score is often collected during or shortly after the intake process, alongside the clinical interview. This number becomes the reference point for everything that follows.
  • At regular intervals. Many programs repeat the questionnaires weekly or every two weeks. Because each form asks about the past 2 weeks, repeating it more often than that means the windows overlap.
  • At treatment team meetings. Scores are one input among several, alongside therapist notes, psychiatric observations, sleep patterns and how a person is participating.
  • At discharge. A final score helps document change and gives the next provider, often an outpatient or step-down program, a starting point.

Some insurers ask for clinical updates during a stay to keep authorizing days. Whether standardized scores are part of that review depends on the plan and the program, so if coverage matters to your planning, ask the program directly what it shares with your insurer.

The Two-Week Window: An Inconvenient Detail Families Rarely Hear

Here is the part that surprises people. Because both questionnaires ask about the past 2 weeks, a score collected on day 7 of a residential stay still partly reflects the week before admission, which is often the hardest stretch. In a 30-day stay, a weekly score only reflects time spent entirely inside the program from about day 14 onward. In practice, that means roughly the final two or three scores of a month-long stay are the ones that describe life in treatment rather than life before it.

This is not a flaw in the tools. It is simply how they were designed. But it explains why an early score can look discouraging even when staff are seeing real engagement, and why a single number in week one is a poor basis for deciding that treatment “isn’t working.”

Why a Score Can Move Without the Underlying Picture Changing

Scores are useful, but they are not a thermometer. Several ordinary factors can push them up or down.

The two-week lookback: early scores carry over symptoms from before admission, so the first comparison is not a clean before-and-after.

Sleep and appetite items: the PHQ-9 includes questions about sleep, energy and appetite, so a structured schedule and regular meals can lower a score before mood itself has shifted much.

Answering style: some people underreport symptoms early because they want to look well, then report more openly as trust builds, which can make a score rise even as treatment is helping.

Medication timing: when a psychiatric medication is started or adjusted, many people need several weeks before the full effect is clear, so scores may lag behind the clinical plan.

Life events during the stay: a hard family conversation, difficult news from home or the approach of discharge can briefly raise anxiety scores.

Clinicians generally look for a pattern across several measurements rather than reacting to one score. That is also the most useful stance for families.

The Question on the PHQ-9 That Gets Special Attention

One PHQ-9 item asks about thoughts of being better off dead or of hurting oneself. In treatment settings, any answer other than “not at all” on that item is typically followed up promptly by a clinician, regardless of the total score. That follow-up is a routine safety step, not a sign that treatment has failed.

If you or someone you love is having thoughts of suicide, call or text 988 to reach the 988 Suicide and Crisis Lifeline, available 24 hours a day. If someone is in immediate danger, call 911 or go to the nearest emergency room. Residential programs are not emergency services and cannot replace emergency care.

What to Ask the Care Team This Week

If your family member has signed a release allowing staff to share information with you, or if you are the person in treatment, these are concrete questions you can bring to your next family session or check-in call. Write the answers down with the date so you can see the trend yourself.

  1. Which standardized measures does the program use, and how often are they given?
  2. What was the admission score, and what is the most recent score?
  3. Which of those scores cover time spent fully inside the program, given the two-week lookback?
  4. Besides scores, what is the team seeing in groups, sessions and daily routines?
  5. What range or change would the team consider meaningful progress before discharge?
  6. Will the scores be shared with the outpatient provider who takes over after discharge?

Asking question 3 is especially helpful. It turns a confusing number into a clear conversation about what has changed since treatment began.

What Scores Do Not Decide

A score alone does not determine when someone is ready to go home, whether a diagnosis is correct or whether a particular therapy is the right fit. Those decisions come from the whole clinical picture: what the person reports, what staff observe, safety considerations, medical factors and the plan for support after discharge. A person can have a moderate score at discharge and be well prepared to step down to outpatient care, and another person can have a low score and still need more support. Measurement is a tool for conversation, not a verdict.

It is also worth remembering that symptom scores measure frequency, not effort. Someone who is working hard in treatment may still report symptoms “more than half the days” for a while. Progress in mental health care is rarely a straight line, and a plateau or a bump does not erase the work that has been done.

How Bodhi Can Help

Bodhi Mental Health supports adults in California and several other states, including the Aptos and San Jose areas, who are living with depression, anxiety, bipolar disorder, PTSD, OCD and panic disorder. If you are weighing residential care and want to understand how progress would be tracked, or you want to check your benefits first, you can verify your insurance online or call 877-883-0780 to speak with our admissions team. We are glad to walk through what the first weeks of care look like and answer questions about measurement, family involvement and next steps.

This article is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Standardized questionnaires such as the PHQ-9 and GAD-7 should be interpreted by a qualified clinician. Always talk with a licensed health care provider about your specific situation. If you are in crisis, call or text 988, or call 911 if someone is in immediate danger.

Close-up of a door lever and deadbolt lock on a bright blue door, representing checking compulsions addressed in exposure and response prevention for OCD

Exposure and response prevention, usually shortened to ERP, is the psychotherapy most closely associated with obsessive-compulsive disorder (OCD). If you or someone in your family is looking at residential mental health care because OCD has started running the day, ERP is the part of treatment you will hear about most and understand least before admission. This guide explains how an ERP plan is built, what a session looks like, and what to ask a program before admission.

ERP for OCD in residential treatment: the short answer

Exposure and response prevention (ERP) is a specific type of cognitive behavioral therapy for obsessive-compulsive disorder in which a person practices facing a feared trigger in planned, gradual steps while deliberately not performing the compulsion that usually follows. The National Institute of Mental Health (NIMH) describes people with OCD as typically spending more than 1 hour a day on obsessions or compulsions, and notes that antidepressants prescribed for OCD can take 8 to 12 weeks before symptoms begin to improve. Because medication can take that long, ERP in a residential setting usually begins in the first days of a stay rather than waiting for medication to take effect, and the practice continues daily under clinical supervision.

Both figures come from the NIMH publication Obsessive-Compulsive Disorder: When Unwanted Thoughts or Repetitive Behaviors Take Over (NIH Publication No. 23-MH-4676, revised 2023, checked October 2026). NIMH also notes that ERP can reduce compulsive behaviors even for people who have not responded well to medication.

Why OCD sometimes needs a residential level of care

Most people with OCD start in outpatient care. Residential treatment is usually considered when rituals have expanded to the point where weekly sessions cannot keep pace. Families often describe the same pattern: showers that run past an hour, a front door that has to be checked so many times that leaving the house becomes a negotiation, or a relative who cannot finish a meal without asking for reassurance again and again.

The practical advantage of a residential setting is time and structure. ERP works through repetition, and a single weekly hour leaves six days in which the old rituals continue unchallenged. In a residential program, exposures can be practiced more than once a day, staff can help with the hard moment right after an exposure. You can read more about how this level of care is organized on our residential treatment page.

How the exposure ladder is built

ERP does not start with the hardest trigger. It starts with a list. In the first days of a stay, the person and their therapist write out the situations, objects, thoughts and images that set off obsessions, along with the compulsions each one triggers. Compulsions include visible rituals, like washing or checking, and invisible ones, like silently repeating a phrase, mentally reviewing a conversation, or asking someone else for reassurance.

Each item is then rated by how much distress it causes, and the list is arranged from easiest to hardest. This becomes the exposure ladder, sometimes called a hierarchy. Many programs also use a standardized rating scale, such as the Yale-Brown Obsessive Compulsive Scale (Y-BOCS), at intake and again later in the stay so progress is measured the same way each time.

A ladder for checking compulsions might start with locking a bedroom door once and walking away, move to leaving a room with a light switch unchecked, and eventually reach leaving the building without returning to confirm the door. The person agrees to every step in advance.

What a single ERP session looks like

An exposure session usually follows the same sequence:

  • Choose the step: The person and therapist pick the next rung on the ladder, one that feels difficult but manageable.
  • Name the prediction: The person states what they fear will happen if they do not perform the compulsion.
  • Make contact with the trigger: The person touches the object, enters the situation, or brings the thought to mind on purpose.
  • Hold off on the ritual: The person stays with the discomfort without washing, checking, counting or asking for reassurance.
  • Review what happened: Afterward, they compare what they feared with what actually happened, and note how the urge changed over time.

The first exposures are uncomfortable by design. NIMH notes that this initial anxiety can create a risk of dropping out of treatment early, and that compulsions decrease for most people as they continue. One of the quieter advantages of residential care is that staff are present in the hours after a hard exposure, when the urge to undo it is strongest.

Why rituals keep OCD going

  • Short-term relief: A compulsion brings brief relief from anxiety, which teaches the brain to reach for the ritual again next time.
  • Untested fears: Every time a ritual is performed, the feared outcome is never tested, so the fear stays intact.
  • Avoidance spreading: Avoiding triggers shrinks daily life gradually, often without the person noticing how much has been given up.
  • Reassurance loops: Answering “Are you sure it’s locked?” works like a ritual performed by someone else, and the question usually returns within minutes.

That last point is where families matter most. Many programs include family sessions that teach relatives how to respond to reassurance-seeking with warmth while declining to answer the question itself.

How medication fits alongside ERP

NIMH describes the most commonly prescribed medications for OCD as antidepressants that act on serotonin, and notes that OCD may require higher doses than are typically used for depression. Dosing and medication choices are decisions for the psychiatric provider, made with the person in treatment, and should never be changed without talking to that provider first.

For people whose OCD has not responded to other treatments, NIMH notes that the FDA approved a form of repetitive transcranial magnetic stimulation (rTMS) for OCD in 2018, extended to standard TMS devices in 2022, used alongside medication, psychotherapy or both. For a general overview of the talk therapies used across mental health conditions, NIMH’s psychotherapies overview is a reliable starting point.

Questions to ask a residential program about OCD care

Not every program that lists “OCD” on its website delivers ERP in a structured way. Ask these on the first call and write down the answers:

  1. Who on the clinical team delivers ERP, and what specific training in ERP do they have?
  2. How many ERP sessions are scheduled per week, and are exposures practiced outside formal sessions too?
  3. How is the exposure ladder built, and which rating scale tracks progress?
  4. How are family members involved, and is reassurance-seeking addressed directly?
  5. How does the program handle triggers that only exist at home, such as a specific kitchen, car or front door?
  6. What does the discharge plan include for continuing ERP with an outpatient provider?

Question 5 matters more than most people expect. An unfamiliar setting can mute some triggers, so gains need to be carried back to the places where rituals started. Our team can walk you through how this works across our treatment programs. Call 877-883-0780 to talk it through.

One thing you can do today

For the next three days, keep a simple log. Each time a compulsion happens, write the time, the trigger, the ritual, and roughly how many minutes it took. Include reassurance questions and mental rituals. At the end of three days, total the minutes per day.

This log does two things. It turns “OCD is taking over” into a concrete picture an assessor can work with, and it shows whether time spent on rituals is approaching or exceeding the hour-a-day mark NIMH describes. Bring it to your next appointment or assessment. If you are also sorting out coverage, you can verify your insurance before that call.

When intrusive thoughts feel dangerous

Some people with OCD experience unwanted, intrusive thoughts about harming themselves or others. Distress about any thought of self-harm deserves to be taken seriously and assessed by a professional, not sorted out alone.

If you or someone you know is struggling or having thoughts of suicide, call or text the 988 Suicide and Crisis Lifeline at 988, or chat at 988lifeline.org. If anyone is in immediate danger, call 911 or go to the nearest emergency room. Residential treatment is not an emergency service. You can also find support and treatment information through SAMHSA.

Getting started

OCD is a long-lasting condition, but it is treatable, and many people regain significant parts of their day once rituals start to loosen. If OCD has grown beyond what weekly therapy can address, a conversation about residential care is a reasonable next step. Call 877-883-0780 to speak with our admissions team about options near you.

This article is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Always consult a qualified health care provider about your specific situation, including any questions about medication. If you are in crisis, call or text 988, or call 911 in an emergency.

Woman sitting on a couch at home researching mental health treatment options on a laptop

Most families start looking for residential mental health care the same way: late at night, on a phone or laptop, typing some version of “mental health treatment near me” and scrolling past ads. Two free federal tools do this job more systematically. One is FindTreatment.gov, the treatment locator run by the Substance Abuse and Mental Health Services Administration (SAMHSA). The other is SAMHSA’s National Helpline. Both are useful, and neither one can tell you whether a specific program is the right fit, has a bed open or takes your insurance. This guide explains how each tool works, what its listings actually represent and which calls to make once you have a shortlist.

If you or someone you love is in immediate danger, call 911 or go to the nearest emergency room. For a mental health crisis or thoughts of suicide, call or text the 988 Suicide and Crisis Lifeline, available 24 hours a day. Veterans can call 988 and press 1. Neither the National Helpline nor a residential treatment program is an emergency service.

What SAMHSA’s National Helpline Is and Is Not

SAMHSA’s National Helpline, 1-800-662-HELP (4357), is a free, confidential treatment referral and information line for people and families facing mental health or substance use conditions. It is open 24 hours a day, 365 days a year, in English and Spanish, and it does not provide counseling: trained information specialists connect callers with state services, intake centers and local treatment options. SAMHSA reports that the line received 833,598 calls in 2020, a 27 percent increase over the 656,953 calls it received in 2019.

A few details from SAMHSA’s own helpline FAQ are worth knowing before you call. The service does not ask for personal information, although the specialist may ask for a ZIP code to find local options. You do not need insurance to use it. People who are uninsured or underinsured are generally pointed toward their state office for publicly funded programs, or toward facilities that use a sliding fee scale or accept Medicare or Medicaid. People with insurance are encouraged to contact their insurer for a list of participating providers. If a phone call feels like too much, you can text a five-digit ZIP code to 435748 (HELP4U); SAMHSA notes that the text service is currently available in English only.

What the helpline will not do is assess the person you are worried about or recommend one program over another based on clinical need. It is a routing service, not an evaluation.

How FindTreatment.gov Works

FindTreatment.gov is SAMHSA’s confidential, anonymous directory of mental health and substance use treatment facilities in the United States and its territories. You enter an address, city or ZIP code and get a map and a list. When we checked the locator on October 5, 2026, its default search radius was 25 miles, and the filter panel included facility type (substance use, mental health or opioid treatment programs) along with options such as “Residential/24-hour residential,” adults, Medicaid, Veterans Affairs and telemedicine.

For anyone looking specifically for residential mental health care, those filters matter. An unfiltered search places outpatient clinics, substance use programs, hospitals and residential programs on the same map, which makes it easy to spend an evening calling places that offer only weekly outpatient appointments.

Why a Listing and a Good Fit Are Different Things

FindTreatment.gov is a starting list, not a vetting service. The locator itself tells users to call a facility before visiting to make sure it provides the services they need. Four structural reasons explain why that step cannot be skipped:

  • Self-reported data: Facility details come from each facility’s own responses to SAMHSA’s National Substance Use and Mental Health Services Survey (N-SUMHSS), not from an inspection by the locator.
  • Update cycle: SAMHSA refreshes listings annually from survey responses, adds qualifying new facilities monthly and posts name, address, phone and service changes weekly only when a facility reports them, so a listing can lag behind what a program offers today.
  • No real-time availability: A listing does not show whether a program has an open bed this week or how long its waitlist runs.
  • No plan-level insurance detail: A payment filter can show that a facility accepts a type of coverage, but not whether it is in network with your specific plan or whether that plan requires prior authorization for residential care.

None of this makes the tool less useful. It simply means the real work moves to the phone once you have names.

A Five-Step Check You Can Run Today

  1. Filter the search. Open FindTreatment.gov, enter your ZIP code, set the facility type to Mental Health and select Residential/24-hour residential. If the list is short, widen the radius; residential programs are far less common than outpatient clinics.
  2. Build a shortlist. Write down three to five programs with each phone number and city.
  3. Call the insurance plan first. Use the member services number on the back of the card and ask three things: Is residential mental health treatment a covered benefit? Is prior authorization required? Which of the programs on my list are in network? You can also verify your insurance with our team.
  4. Call each program with the same four questions. Do you treat this primary condition, such as bipolar disorder, PTSD or OCD, in a residential setting for adults? Do you have availability now, and if not, what is the expected wait? Are you in network with this specific plan? Who completes the admission assessment, and how soon can it happen?
  5. Date every answer. Write down the date, the program and the name of the person you spoke with. Availability and insurance answers change from week to week, and a dated note saves you from repeating the same call.

What Families Tend to Notice on These Calls

Many families expect to be asked about the program they are interested in and are surprised by how quickly the conversation turns to the person who needs care. Intake staff usually want a picture of current symptoms, current medications, any recent hospital stays and how daily life has been going over the past few weeks. Having a written medication list and a short timeline of recent months on hand makes each call shorter and the answers more useful.

Another common moment: a program asks to speak with the person directly. Residential mental health programs generally admit adults on a voluntary basis, so intake staff often need to hear from the person who would be attending before scheduling an assessment. That can feel like a setback for a worried parent or partner, but it is a normal part of the process. If the person is not ready yet, it can still help to gather the information so the path is clear when they are.

It is also common to hear “we do not treat that here” or “our next opening is several weeks out.” That is information, not rejection. It narrows the list, and it is exactly why the dated notes from the five-step check are worth keeping.

Where Residential Care Fits

Residential treatment is one level of care among several. It is generally considered when symptoms of depression, anxiety, bipolar disorder, PTSD, OCD or panic disorder make it hard to keep up with daily life, and outpatient care has not been enough on its own. Our page on residential mental health treatment explains how it differs from outpatient programs. The National Institute of Mental Health also keeps a plain-language guide to getting help for mental illnesses that covers immediate crisis options alongside other ways to find care.

If someone is talking about wanting to die, has a plan or cannot stay safe, that is not a moment for comparing directory listings. Call or text 988, or call 911 for immediate danger.

When You Want a Second Set of Eyes

Federal tools are a good way to see what exists near you. Turning that list into a decision is a different job. Our admissions team can talk through what you have found, explain how our residential programs in Aptos and San Jose approach care, and help sort out insurance questions before you commit to anything. Call 877-883-0780 to talk it through. If you already know residential care is the next step, call 877-883-0780 and we can walk you through what admission involves.

This article is for educational purposes only and is not medical, legal or insurance advice. It does not replace an evaluation by a licensed mental health professional. Treatment decisions should be made with a qualified clinician who knows the individual’s history. If you or someone you know is in crisis, call or text 988 or call 911 in an emergency.